Again, I am fascinated by how some physicians order an "IBD panel" in a kid with abdominal pain to r/o Crohn's disease (CD) or Ulcerative colitis (UC). Unless I am confused, an IBD panel's role is to help differentiate the two types of IBD, and not make the diagnosis (substantial false positives and false negatives).
Here is some information I found useful:
Main laboratory markers:
ANCA: anti-neutrophil cytoplasm antibody
ASCA: anti-Saccharomyces cervisiae antibody
Anti-OmpC: anti E coli-related outer membrane porin C
Anti I2
Anti-Cbir1: antibody against flagellin
pANCA present in two thirds of UC patients and one third of CD
pANCA-positive CD patients have a clinical picture similar to UC
ASCA (IgG or IgA) present in half of patients with CD
High titers of ASCA in the absence of pANCA highly predictive of CD
Antibodies to OmpC and I2 are associated with more strictures and internal perforations
Anti-Cibr1 associated with CD, particularly penetrating disease, fibrosing disease, and SB involvement.
pANCA positive CD patients less likely to respond to inflixamab than ASCA positive or totally seronegative
Reference:
Wyllie R, Hyams JS, Kay M (2011). Crohn's Disease. In Wyllie R, Hyams JS, Kay M (Edx.), Pediatric Gastrointestinal and Liver Disease 4th ed (pp 462-489). Elsevier.
T
This publication from the Mayo clinic is concise and useful too.
Sunday, February 20, 2011


Saturday, February 5, 2011
Neonatal testicular torsion: what are the options?

This read stemmed from a hallway conversation I had with my favorite French-Canadian urologist (and not because he's the only FCU I know). I had been under the impression that, unlike ovarian torsion (where you detorse the ovary and give it a chance regardless of how it looks because of the possibility of viable tissue surviving), an orchiectomy for testicular torsion with ischemia was mandatory. The rationale behind that is the theory that leaving a necrotic testicle behind results in contralateral testicular injury. This injury results from an autoimmune response that occurs because of a breach in the hematotesticular barrier on the ischemic side. Well, that turned out to be erroneous thinking.
Djahangirian et al discussed this subject in a recent outcome study from Quebec and noted that the concern for the breach of the hematotesticular barrier applies to pubertal boys only (I should have figured that one out myself, given that you need sperm to form antisperm antibodies!!). Their main discussion was regarding the different management options for neonatal testicular torsion (NTT), which is defined as torsion detected within 30 days of birth, and constitutes 5% of all cases of testicular torsion. They discussed management rationales for the affected testicle as well as the contralateral one (which is presumed to be at risk of torsion too). Regarding the management of the torsed testicle, they noted that a prenatally torsed testicle (which constituted 50% of their cases) had no chance of survival so emergent surgery in an attempt to salvage the testicle was not recommended, and the options were elective orchiectomy or observation. In cases where the torsion occurs postnatally (the other 50%), and because of a slim chance of salvage (mostly in patients who present with signs of discomfort only), emergent exploration was indicated.
As to the management of the contralateral testicle (which they noted could torse in 5% of cases, either synchronously or metachronously), they suggested that elective orchidopexy, and even observation with strict instructions to the parents regarding the signs of torsion, were viable options.
Between medico-legal concerns and guaranteed sleepless nights, observation of the contralateral testicle does not sound like a reasonable option to me, so I would stick to an exploration with orchiectomy and contralateral pexy.
Timing of surgical management of neonatal testicular torsion. Djahangirian et al. Journal of Pediatric Surgery (2010) 45, 1012-1015
Saturday, January 29, 2011
Spleen/Liver injury: Grade + 1 = days of bed rest; What is the current status?

Phone conversation with R3 on call:
R3: got a kid down here, has grade 4 splenic lac. Stable
Me: so, what do you want to do?
R3: "take it out"
To be fair, the kid did "collapse" on the way to the bathroom, but probably form a vagal response.
Obviously, very few Pediatric Surgeons would argue that non-operative management is the general strategy in a stable child with blunt liver or splenic trauma. What constitutes non-operative management, on the other hand, is slightly more controversial.
Until recently, we had been treating kids with liver and splenic injury with bed rest, where the days in bed were determined by the grade of the injury. Grade + 1 = days in bed (grade + 2 = weeks of limited activity). In this protocol, as pointed out by St Peter et al. in a paper published in this month's JPS, days of bed rest are considered treatment variables, suggesting that a Grade 3 splenic lac needs 4 days to stabilize. Recent literature on the subject of non-operative management of liver and splenic injury has shifted focus from an absolute grade-defined management algorithm to one determined by hemodynamic stability and physical findings in an attempt to safely truncate what some would concider to be an overkill in terms of hospital stay.
St Peter et al prospectively studies 131 patients with liver and splenic injury from blunt trauma and noted that a protocol for monitoring (not therapy), where stable patients with grades I or II splenic injury are monitored for one night (defined as spending a night in their room regardless of time admission), while those who had a grade III or more, spend two nights in the hospital, is a safe alternative that could shorten hospital stay. Based on their protocol, if a patient needed a transfusion, the clock on observation was re-zero'd.
Using this protocol, the splenic salvage rate was 98.7%, regardless of associated injuries and transfusion requirements (13% required blood transfusion for their splenic and liver injuries). Obviously, and based on this protocol, there was a substantial decrease in hospital stay requirements.
St Peter et al. Prospective validation of an abbreviated bedrest protocol in the management of blunt spleen and liver injury in children. Journal of Pediatric Surgery (2011) 46, 173-177
Wednesday, January 19, 2011
What is the significance of CT-only lung lesions in Wilms' Tumor

The advent of CT imaging of the chest as part of the work up of Wilm's tumor has created substantial controversy. It is natural to assume that lesions of the lung found on CT scan,in the setting of a known primary tumor, represent metastatic disease. False. A study by Ehrlich et al, from the National Wilms' Tumor Study 5 showed that up to a third of lung lesions found on CT only (negative CXR) were not malignant (by pathology). This raises the question of how CT-only lesions should change the management.
Based on COG recommendations, patients who are local stage I or II FH Wilms' tumor should undergo biopsy of CT-only lung lesions to gauge therapy. Patients with Stage III or IV disease, who are enrolled in AREN0533 trial (evaluating response of lung lesions to 3 drug therapy after 6 weeks) are not treated differently in the presence of lung lesions unless these lesions persist after 6 weeks, at which time they would be treated with additional lung radiation, preferably after confirming their malignant nature with biopsy.
Erlich PF. The value of surgery in directing therapy for patients with Wilms’ tumor with pulmonary disease. J Ped Surg (2006) 41, 162-167
Sunday, January 2, 2011
"We may need to recannulate this CDH baby!"

That's probably the last thing one wants to hear after answering a page!
Fortunately, the kiddo is doing better and did not require a second ECMO run (near diaphragmatic agenesis). This prompted a search for some literature on the subject of second run ECMO. Took a bit of research but found an article by Meehan et al. that looked at 205 patients from the ELSO neonatal registry who underwent multiple ECMO runs.
My main concern whenever the subject of potential need for recannulation comes up is the issue of recannulating the right CCA and CJV (A scenario encountered in 56% of patients in this study), with the potential for embolic events.
In their review, the authors noted a 20% increase in complication rates, with the largest increase in complication rates being for neurologic (134% increase) and infectious complications (79% increase). The most common type of neurologic complications were clinical seizures and radiologically documented cerebral strokes.
Overall survival after a second run was 38% (32% for CDH).
Journal of Pediatric Surgery, Vol 37, No 6 (June), 2002:pp 845-850
Friday, December 10, 2010
PDA ligation controversies
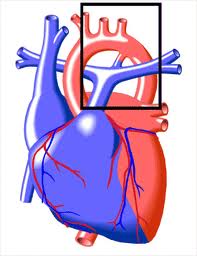
Well, that was another excellent joint neonatal-Pediatric surgery conference at WCHOB. The subject was PDA and the discussion included basic PDA physiology, morbidity, treatment strategies, post ligation syndrome, and most importantly looked at the evidence (or lack of) supporting the need for PDA ligation.
The discussion began with the general principles of PDA physiology, including the normal role of prostaglandins produced by the placenta and the high intraluminal blood pressure in the ductus (secondary to high pulmonary vascular resistance) in keeping the ductus patent in utero. Normal term delivery reverses these factors and results in closure of the ductus initially by smooth muscle constriction then then anatomic remodeling.
The clinical consequences of a PDA are a result of the left to right shunt, and subsequent change in blood flow to vital organs with subsequent metabolic acidosis, increased risk of IVH and NEC secondary to diastolic steal, and pulmonary vascular disease due to continuous dilation of pulmonary vessels during diastole.
The main strategy for prophylaxis and treatment is the administration of Indomethacin, and when that fails, surgical ligation.
The first issue that comes up is the evidence for the need for the prophylaxis and treatment of PDA.
The literature supports the benefit of the prophylactic use of indomethacin for it's effectiveness of PDA closure, decrease the need for surgical ligation, decrease in the incidence and severity of pulmonary hemorrhage, and decrease in incidence of grade 3 and 4 IVH.
Indomethacin, however, is not innocuous. It can cause a transient change in renal function, increases the risk of GI perforation when administered simultaneously with steroids. It was not found to have any neurodevelopemental effects.
So why should a PDA be treated? A study looking at infants <1500 g showed an 8 fold increase in mortality in the presence of a PDA.
When it came to the subject of surgical ligation of PDA, the data was much less convincing and somewhat troubling. Studies not only shed doubt on the proposed rapid improvement of cardiovascular parameters (Raval et al. J Ped Surg 2007.42(1):69), some actually showed that surgical ligation may be associated with an increased risk of BPD, severe ROP, and neurosensory impairment in ELBW infants (Kabra et al. J Peds 2007;150:229).
Finally, the subject of post ligation cardiac dysfunction was addressed. This results from ligation of the PDA, which results in a sudden switch from volume to pressure overload on the heart which was, as a baseline, subjected to impaired coronary perfusion (form diastolic steal with a PDA), and preexisting pulmonary edema and cardiac failure. Post ligation cardiac dysfunction presents with severe hypotension, failure of oxygenation, and myocardial dysfunction. The hemodynamic profile shifts from pre ligation state of a high preload/low after load and myocardial ischemia from decreased diastolic perfusion, to post ligation state of a sudden increase in after load, decreased LV end diastolic volume, and decreased LV output.
Importantly, the extent of post ligation dysfunction depends on pre ligation hemodynamic, with some authors supporting the prophylactic use of milrinone when the pre ligation LV output is < 200 ml/kg/minute.
As to the management of post ligation cardiac dysfunction, the strategy is to use inotropes that do not increase after load (Milrinone/dobutamine), optimize oxygen carrying capacity, and fluid management.
The upshot on PDA interventions was that prophylactic ligation does not improve outcome, indomethacin prophylaxis decreases IVH and need for PDA ligation, indomethacin prophylaxis does not improve neurodevelopemental outcome in survivors, earlier Indomethacin treatment is associated with higher rates of DA closure. As to the ideal timing of medical or operative closure, that remains to be clarified.
With the current available data, many questions remain unanswered:
can we identify infants whose ductus will close spontaneously?
can we reduce the number of doses of indomethacin without compromising outcome?
Saturday, November 13, 2010
Perforated appendicitis: an evidence-based definition
Papers that cause the coveted “ahah!” feeling are very few and far-between. But this one certainly made me go ahah!
In this paper, the authors set out to unify the definition of perforated appendicitis. They pointed out that since the definition of perforation was all over the board, no true conclusions could be made of studies looking at outcome.
The authors defined perforation as the presence of a visible hole in the appendix or the finding of an extruded appendicolith (this definition was used for a prior study they performed). Patients with purulent fluid in the peritoneal cavity who did not have a visible hole as well as patients with a gangrenous appendix were considered non-perforated. Patients in the perforated appendicitis group received a prolonged course of postoperative antibioitcs while those in the non-perforated group received only preoperative antibiotics. The authors then studies the effect of this strict definition on patient outcome, including the rate of intraabdominal abscess formation.
The results were very interesting. Expectedly, the rate of postoperative abscess formation in the perforated group increased from 14% to 18%. This made sense since the denominator in the perforated group was smaller with this strict definition. More importantly, the rate of abscess formation in the non-perforated group decreased, from 1.7% to 0.8%. This was the most important finding in this study. This confirmed that withholding postoperative antibiotics from patients with a gangrenous appendix, or those with “puss” in the abdomen but no true hole, did not result in worse infectious complications.
Defining perforation in clear simple terms, and showing that this definition works, should help prevent unnecessary antibiotic administration, waste of resources, as well as inter-study inconsistencies.
St Peter et al. An evidence-based definition for perforated appendicitis derived from a prospective randomized trial. J Ped Surg (2008) 43:2242-45
Subscribe to:
Posts (Atom)